Saturday, April 14, 2012

Wound Neovascularization with Dermal Substitutes

April 14, 2012

This is the second of 2 articles detailing wound healing studies done in nude mice implanted with different biological materials.  Full thickness skin wounds were created on the dorsum and then different dermal replacements were implanted.  Healing was followed for 28 days and very detailed histological and immunostaining evaluations of the wounds were performed to quantify the healing process.  Most studies of wound healing use simple or highly subjective measures of healing, but one of the main goals of these studies was to use objective criteria to quantify healing and to do so in fine detail.

Below is the full text of this article and also a PDF link of higher quality.


Wound Neovascularization and Dermal Substitutes in Nude Mice


Neovascularization of Wounds Treated with Dermal Substitutes in Nude Mice

by


Michele M. Loor, MD, Anh-Tuan Truong, MD, Barbara A. Latenser, MD 1,2,3 ,

Dorion E. Wiley, MD 1,2, and Robert J. Walter, PhD 1,2


1 Sumner L. Koch Burn Center, Department of Trauma, John Stroger Jr. Hospital of Cook County  &

2 Department of General Surgery, Rush University Medical Center, Chicago, Illinois

3 Current address:  Director, Burn Unit, University of Iowa, Iowa City, IA


Address Correspondence to:

Robert J. Walter, PhD
Department of Trauma, Suite 1300
John Stroger Jr. Hospital of Cook County
1900 West Polk Street
Chicago, IL 60612

Phone:  312.864.0578

ABSTRACT


Background:  Dermal substitutes implanted into full-thickness skin wounds reduce wound contraction, improve cosmesis, and improve function.  These effects depend upon the development of optimal vascularization of the dermal substitute.

Study Design:  Full-thickness skin wounds were created on the dorsum of nude mice.  A dermal matrix (Integra®, AlloDerm®, acellular dermal matrix, Dermalogen®, or Dermagraft®) was implanted and covered by a mix of fibrin glue (FG) and human keratinocytes.  Wound healing was observed for 4 weeks.  Biopsies were immunostained for laminin followed by blood vessel quantitation using image processing.  Vessels were quantified in the superficial and deep dermis from the wound center, wound margin, and from peripheral unwounded dermis.

Results:  Extensive vascularity was seen at day 28 in implanted Dermagraft® and Dermalogen®.  AlloDerm®, ADM, and Integra® showed slower vessel ingrowth from the wound base and margins and, by day 28, showed diminished wound contraction. The average vessel size in wounds treated with Integra was greater than normal at both days 14 and 28.

Conclusions:  Dermagraft® and Dermalogen® underwent extensive granulation whereas AlloDerm®, Integra®, and ADM showed a more controlled, progressive vessel ingrowth.  For AlloDerm® and ADM, this pattern was associated with reduced wound contraction and increased epithelialization.

Keywords: neovascularization, dermal substitutes, wound healing, nude mice, fibrin glue
Abbreviations:  ADM: acellular dermal matrix, FG: fibrin glue, KC: keratinocytes, ACIS: automated cellular imaging system, WC: wound center, WM: wound margin, NP: normal peripheral tissue


INTRODUCTION

The treatment of full-thickness skin wounds poses a significant clinical challenge.  An open wound not only provides a portal of entry for microorganisms, but it also allows vital fluid and electrolytes to escape. The primary objective in treating an open wound is, therefore, early coverage.  Secondarily, healed wounds must be optimized for  function and appearance.  Full-thickness wounds lack a dermis and dermis regenerates poorly or not at all.  As a result, these wounds heal slowly with significant scarring and contracture.  Various synthetic collagen-based dermal matrices are now available for use in wounds.1-11  Dermal replacements have space-filling properties and are intended to provide rapid wound coverage. They must also permit host cell infiltration and controlled neovascularization so that the dermal substitute may be quickly incorporated into the wound and subsuquently remodelled to form dermis that is as similar to unwounded dermis as possible.  However, the efficacy of the available dermal substitutes materials in the treatment of full-thickness wounds has, with the exception of our recent studies12,13, seldom been carefully compared.

In most cases, placement of a dermal matrix is later followed by split-thickness skin grafting to provide definitive wound closure. The use of cultured autologous keratinocytes (KCs) has been studied extensively as an alternative to autografting, particularly in patients with greater than 40% total body surface area wounds who have limited donor site availability.14-21 Several methods of KC delivery to wounds are available including combination with a fibrin sealant 22-26 and application via a spray apparatus.27-32  We have developed a spray method for applying KCs suspended in fibrin sealant to the wound surface.  In vitro and in vivo tests show that the viability and proliferative potential of the sprayed KCs remains very high.

Neovascularization is a key step in wound healing.  It is a complex process that is dependent upon appropriate interactions between the extracellular matrix, the migrating endothelial cells, and a number of growth factors.  Dermal substitutes composed of native (undenatured), allogenic extracellular matrix such as acellular dermal matrix (ADM) and AlloDerm® become readily vascularized, complement healing, and reduce contractive scarring in a variety of wound types.  We hypothesized that the mode and rate of neovascularization during the process of wound healing in the presence of ADM or AlloDerm® may be important determinants in final wound resolution.  The process of wound vascularization may be significantly altered with materials such as Integra®, Dermalogen®, and Dermagraft® which contain synthetic, highly modified, or denatured substances that may negatively affect wound resolution.

To evaluate this, dermal substitutes in conjunction with FG and KCs were introduced into full-thickness wounds on the dorsum of nude mice.  Paraffin-embedded sections from weekly biopsies were immunostained for laminin, an antigen found in the endothelial basement membrane, to assess and compare vascularization in these healing wounds.  The progress of wound healing and particularly dermal neovascularization was evaluated quantitatively over a period of four weeks based on digital imaging and analysis software. 

METHODS AND MATERIALS


      The following materials were used:
§         Tisseel® (Baxter Health, Deerfield, IL) is a two component system in which fibrinogen, calcium, thrombin, and a protease inhibitor are combined and dispensed onto a wound or other surface to form a fibrin clot.
§         Integra® (Ethicon, Somerville, NJ) is a bilayer artificial skin composed of a “dermal” layer of bovine collagen gel cross-linked with shark chondroitin-6-sulfate and an “epidermal” layer of polysiloxane polymer (which was removed for this study).  Integra® is indicated for partial-thickness wounds, but is being used increasingly for full-thickness wound treatment.
§         AlloDerm® (Lifecell Corp., Branchburg, NJ) is an undenatured collagen matrix derived from human skin that is treated to remove most of the cellular components.
§          Acellular Dermal Matrix (ADM) is a native dermal collagen matrix derived from human skin that is treated to remove all cellular components.  The preparation and characterization of this matrix material has been described previously 11,33. Briefly, human cadaver skin was treated with Dispase to remove epithelial cells and then Triton-X detergent to remove all residual cells and cellular debris. 
§         Dermalogen® (Collagenesis Corp, Beverly, MA) is a powdered human dermal collagen matrix that has been treated to remove some cellular components and is used primarily for aesthetic surgery.
§         Dermagraft® (Smith & Nephew, Largo, FL) is comprised of a woven bioabsorbable polymer on and in which human dermal fibroblasts are grown and then devitalized.  This material is indicated for treating full-thickness wounds. 

Animals and Surgery

NIH homozygous male nude mice, 4 weeks of age (Taconic, Germantown, NY) were used. All surgical interventions were performed in the John H. Stroger, Jr. Hospital of Cook County Animal Facility using protocols approved by the IACUC.  Preoperative Kanamycin (25U/kg IM) was administered to the animals and ketamine/ xylazine was used for anesthesia.  Under aseptic conditions, 2 cm x 2 cm full-thickness wounds were excised down to the muscle fascia and then implanted with: 1) Integra®, 2) AlloDerm®, 3) ADM, 4) Dermalogen®, 5) Dermagraft®, 6) KCs + FG only, or 7) FG only.  Each group was comprised of at least 6 mice, three of which underwent weekly biopsies.  In the groups of mice that received dermal substitutes, the substitute was cut to size and sutured into the wound using 4-0 nylon sutures.  In the Dermalogen® group, 0.75 cc of the viscous suspension was placed into the wound.  Animals in groups 1-6 received human KCs sprayed onto the dermal substitutes or wound surface in combination with FG.  KCs (4 X 10⁵/ cc) were suspended in the thrombin component of Tisseel® and were sprayed such that the final number of KCs applied to each wound was 2 X 10⁵ in 1.0 cc of FG.  All defects were covered with a semi-permeable adhesive film (Op-Site, Smith & Nephew, Largo, FL), Xeroform (Sherwood Medical, St. Louis, MO), dry cotton gauze (Adaptic, Johnson & Johnson, New Brunswick, NJ), and finally with a fine stainless steel mesh fixed to the animals’ back with skin sutures.  This last was used to prevent the wounds from being disturbed by chewing or scratching.  The dressings were inspected daily.  Biopsies were performed on designated animals at 7, 14, 21, and 28 days post-surgery. The harvested biopsies were fixed in 10% buffered formalin, paraffin embedded, and sections stained with H&E or immunostained.34 

Human KC Culture and Preparation for Spraying

Human KCs, Epilife culture medium, supplements, and transfer solutions were obtained from Cascade Biologics (Portland, OR).  Cells were grown in 75 cm2 flasks from expanded frozen stocks stored after the second passage.  After 7-10 days of proliferation and growth, flasks containing 50-80% confluent KCs were washed, trypsinized briefly to release cells from the substrate, trypsin was neutralized, and the suspension centrifuged at 20xg for 5 min and 4ºC.  The supernatant was discarded and the cells resuspended in fresh Epilife medium. Cells were mixed with the reconstituted thrombin/calcium component of the fibrin sealant kit at a 1:1 dilution.  The fibrinogen component was also reconstituted and diluted 1:1 with Epilife.  This components was stored at 4ºC until being sprayed onto wounds in conjunction with the fibrinogen component using a tuberculin syringe fitted with a spray head as indicated above.34  

Immunostaining

Tissue sections were deparaffinized and antigen retrieval was performed by incubating specimens in pepsin (1mg/ ml 0.01N HCl) at 37ºC for 2 hours.  Following this, nonspecific binding was blocked using 1% bovine serum albumin and sections were then incubated in rabbit anti-mouse laminin IgG (Sigma, St. Louis, MO) at a 1:10 dilution followed by HRP-conjugated goat anti-rabbit IgG secondary antibody (Cappel, Irvine, CA) at a dilution of 1:100.  Reaction product was generated using a Vector DAB/peroxide Developing Kit (Vector, Burlingame, VT) according to the manufacturer’s specifications with a 10 min developing time and specimens were counterstained with hematoxylin QS (Vector, Burlingame, VT).  Normal skin from previously unwounded mice was also immunostained for laminin to serve as a control.  Laminin staining marked the basement membrane of epidermis, nerve, muscle, and vessels.  Within the dermis, immunostained structures showing an open lumen were counted as blood vessels.  These were readily distinguished from the other positively stained structures by their location and morphology. 

Data Analysis

Wound characteristics were measured grossly and histologically.  Gross observations were made at days 7, 14, 21, and 28 post-surgery.  Wound contraction and degree of epithelialization were measured using UTHSCSA ImageTool software in conjunction with digital photographs of wounds  Vessel quantification was performed using the ChromaVision (San Juan Capistrano, CA) Automated Cellular Imaging System (ACIS) in conjunction with microvascular density (MVD) software.  Vessels were counted in the superficial (papillary) dermis, i.e., the region of dermis directly beneath the epidermis, and in the deep (reticular) dermis, i.e., immediately above the hypodermis.  Three different zones of each wound biopsy were evaluated in this way: the wound center (WC), wound margin (WM) and unwounded normal dermis (NP) peripheral to the wound margin.  Zone selection was standardized by defining: WC as the region equidistant from each wound margin; WM as the area directly adjacent to unwounded tissue; and NP as the area with normal skin structures and appendages at least 500 um away from the wound margin. Data obtained by image analysis included the microvascular density (number of vessels/ mm2) and the vessel area (µm2/ vessel) based on laminin immunostaining.   Results were analyzed by one-way ANOVA with Tukey’s post tests.


RESULTS
Gross wound observations

Each of the dermal substitutes except Dermalogen® reduced the amount of wound contraction as compared to wounds that received only sprayed KCs + FG (figure 1).  Thirty-five to 45% wound contraction was observed in wounds implanted with AlloDerm®, Dermagraft®, Integra®, or ADM at 28 days post-operatively.  Greater contraction (60%) was observed in the Dermalogen® and KCs + FG groups (figure 2).  Dermagraft®-implanted wounds showed poor epithelialization and poor incorporation into the wound with contraction limited only as long as the implant was retained.  Often Dermagraft® implants underwent partial or total spontaneous dehiscence and were rejected from the wound.

Laminin Immunostaining and Vessel Counts

Vessel counts were performed on immunostained sections from biopsies taken on days 14 and 28 (figures 2 and 3).  Six different regions were scored for each section: wound center, superficial and deep; wound margin, superficial and deep; normal peripheral dermis, superficial and deep.  For some parts of the analysis superficial and deep counts were combined to yield total counts representative of each region.  The primary control in this study was skin from previously unwounded animals (CTL) for which vessel counts in the superficial and deep regions were performed.  For each of the groups, additional internal controls were included by analyzing the number of vessels in the normal peripheral tissue flanking the wound.  For most of the experimental groups, this tissue exhibited vascularity similar to that of CTL skin. 
During the 28 day study period, the number of vessels seen in the superficial dermis rose from low levels at day 14 to supernormal levels at day 28 for Dermagraft® (p<0.05 vs CTL, one-way ANOVA,Tukey’s post tests) and Dermalogen® (figure 4).  Hypervascularity was seen in the superficial dermis for the KC + FG group beginning at day 14 with little change in vascularity between days 14 and 28.  AlloDerm®, ADM, and Integra® all showed minimal vascularity in the superficial dermis at day 14 (p<0.01 for ADM and AlloDerm vs CTL, p<0.05 for Integra vs CTL).  By day 28, the number of vessels in each of these groups approached the normal level but still remained somewhat hypovascular.

Similar patterns were seen for the number of vessels in the deep dermis over time (figure 5).  For AlloDerm®, there was limited vessel ingrowth in the deep dermis at day 14 (p<0.05 vs CTL)  and low levels at day 28.  The Integra® and ADM groups demonstrated an initial rise in vascularity at day 14 followed by a decrease in vessel number on day 28, such that both groups were ultimately hypovascular.  In contrast, the Dermagraft®, Dermalogen®, and KC + FG groupswere hypervascular  at day 28.  With regard to total vascularity (superficial + deep) at day 28, some of the dermal substitute groups were clearly hypervascular (Dermagraft®, p<0.001, and Dermalogen®, p<0.05) while others were hypovascular (Integra®, AlloDerm®, and ADM) compared to normal skin (CTL) (table 1). 

Vessel Area

The average area per blood vessel was also determined using the ACIS system for vessels present in the superficial and deep regions of the wound center.  The average vessel area in control normal mouse dermis (CTL) was used as the standard to which the values for implanted skin substitutes were compared. In the superficial dermis, larger than normal vessels were seen at day 14 for Integra (p<0.001 vs CTL), KC + FG, and AlloDerm.  In contrast, Dermagraft, Dermalogen, and ADM had smaller than normal vessels at day 14 (p> 0.05).  By day 28, vessel caliber for each of the groups approached normal with no significant differences from CTL, with the exception of Integra, which had persistently large vessels in the superficial region (p<0.01) (figure 6).  This same feature of large caliber vessels was also seen in the deep dermis of wounds treated with Integra at days 14 (p<0.01) and 28 (p<0.05) (figure 7).  In all other groups, vessel size was similar to CTL at both time points.

Degree of Epithelialization

            Digital imaging and analysis were used to determine the percent of the original wound area which was reepithelialized at days 7, 14, 21, and 28 (figure 8).  Wounds treated with AlloDerm,  ADM, and Integra underwent approximately 40% epithelialization by day 28.  In contrast, wounds treated  with Dermalogen or Dermagraft were less epithelialized (20% of original wound) at the conclusion of the study. Wounds treated with KC + FG alone were 35% epithelialized at day 28. 


DISCUSSION

Angiogenesis is integral to effective wound healing.  Blood vessels deliver oxygen, nutrients and inflammatory cells into the wound and provide conduits for the removal of metabolic by-products and debris from damaged tissue.  Appropriate angiogenesis is a complex process that involves endothelial cell division, selective degradation of vascular basement membrane and of surrounding extracellular matrix, and endothelial cell migration.35  The level of organization of the extracellular matrix plays a key role in the regulation of neovascularization in that it provides support for migrating endothelial cells and acts as a reservoir for endothelial cell growth factors derived from the plasma or serum and from infiltrating fibroblasts, leukocytes, and migrating KCs.36  It is thought that full-thickness wounds should undergo an initial phase of vigorous angiogenesis that is later followed by vessel regression, such that the final pattern of vascularization is similar to that of normal skin.37

            However, no studies have been published directly comparing wound healing seen with different commercially-available dermal substitutes.  Thus, it is difficult to objectively determine which dermal substitutes are most useful in the treatment of full-thickness wounds.  Within this context, there are few studies which have examined the process of neovascularization in wounds implanted with dermal substitutes.  We hypothesized that wounds implanted with dermal substitutes composed of undenatured, allogenic extracellular matrix such as ADM and AlloDerm®, wound be readily incorporated and develop vascularization more similar to normal skin than dermal substitutes composed of synthetic, non-native, or denatured substances such as Integra®, Dermalogen®, and Dermagraft®.  To a large extent, this hypothesis was confirmed by the data presented here.

Grossly, wounds implanted with ADM, AlloDerm®, or Integra® demonstrated less wound contraction losing about 40% of their original size by day 28 and better cosmetic results than did Dermagraft®, Dermalogen®, or KC + FG only.  Our findings indicate that, of the dermal substitutes with native compositions, ADM and AlloDerm® underwent a gradual and limited pattern of neovascularization and were ultimately somewhat hypovascular at day 28.  In terms of vessel size, wounds treated with ADM and AlloDerm contained vessels of a caliber similar to CTL at both day 14 and 28.  For the highly modified or synthetic dermal substitutes, Dermagraft® and Dermalogen® (and KCs + FG alone), vascularization proceeded rapidly resulting in hypervascularity by day 14 or day 28. The size of the vessels in these wounds was also similar to CTL on days 14 and 28.

The results for Integra® were noteworthy in that despite its denatured, highly modified composition relative to normal dermis, it underwent a controlled pattern of vessel ingrowth that appeared to be conducive to improved wound healing.  This seems to confirm the previous claims that the collagen-GAG matrix of Integra® has been specifically designed to have pore sizes that ensure adequate microvascularization of the forming neodermis.38-40 Notably, wounds in the Integra group contained vessels of  significantly larger areas than CTL at both days 14 and 28.  Upon further review of these specimens, it appears that they contain an unusually large number of tortuous vessels that are oriented perpendicularly to the wound surface.  These features may cause the vessel area calculations performed here to be skewed toward large vessel areas since more vessels were cut in longitudinal or tangential section due to their orientation in the tissue. This feature of Integra is likely related to the design of the Integra matrix, with the orientation of the pores allowing vessel growth in this configuration.  This result may be related to the improved wound healing observed with the use of Integra and clinical observations showing its ability to support overlying skin grafts. 

 Wounds in the Dermagraft® group demonstrated extensive granulation which may, to some extent, be attributable to its content of non-viable fibroblasts that may act as a source of vascular endothelial growth factor (VEGF).  Similarly, when viable fibroblasts are added to de-epidermized dermis, enhanced wound vascularization has been shown.42  However, the present study illustrates that too much neovascularization can also result in impaired wound healing.  In the Dermalogen® and Dermagraft® groups hypervascularity at day 28 correlated with increased wound contraction and poor wound cosmesis.  Overall, there seems to be an optimal rate and final level of vascularization in healing wounds, where either increased or decreased rates or levels are associated with suboptimal healing. 

These results with Integra® and Dermagraft® also point up one important aspect of wound healing could not be tested in this model.  The model is insensitive to the xenogenic (in this case, non-mouse) nature of some of the components of these dermal substitutes because of the T cell immunodeficiency that characterizes nude mice.  Of course, it is this immunodeficiency that makes a study such as this possible.  Nonetheless, aspects of inflammation that might be triggered in humans by the presence of allogenic or xenogenic materials such as shark chondroitin sulfate, bovine collagen, or human fibroblasts are not seen in this model.  Interestingly, the dermal substitutes that contain such materials do not seem to evoke a strong immune response in humans.

Clinical experience tells us that certain minimum amounts of wound vascularization must be present and certain maximum amounts of granulation tissue may be tolerated for implanted skin grafts to survive.  The present study shows that the composition of implanted dermal substitutes can affect angiogenesis.  This will undoubtedly determine the level of oxygenation and the growth factor milieu (EGF, FGF, PDGF, VEGF, etc.) in the dermis.  Dermagraft® and Dermalogen® underwent extensive granulation, whereas AlloDerm®, Integra®, and ADM underwent limited vessel ingrowth that seemed to be conducive to the development of normal dermal structure, reepithelialization, and minimal wound contraction.  These data indicate that the rate and final extent of vascularization are important determinants in the efficacy of dermal substitution for the treatment of full-thickness wounds.  Further efforts to achieve one-step full-thickness wound closure will depend upon the use of dermal substitutes that can vascularize rapidly enough to support overlying KCs or an ultra-thin split-thickness graft, but will not induce overly abundant granulation tissue formation.  This is a realistic goal using currently available biomaterials but further refinements are needed to achieve optimal healing.


REFERENCES

1.      Burke JF, Yannas IV, Quinby WC, Bondoc CC, Jung WK. Successful use of a physiologically acceptable artificial skin in the treatment of extensive burn injury. Annals Surg. 1981; 194: 413-427.
2.      Hansbrough JF, Boyce ST, Cooper ML, Foreman T. Burn wound closure with cultured autologous keratinocytes and fibroblasts attached to a collagen-glycosaminoglycan substrate. JAMA. 1989; 262: 2125-2130.
3.      Boyce ST, Greenhalgh DG, Kagan RJ, et al. Skin anatomy and antigen expression after burn wound closure with composite grafts of cultured skin cells and biopolymers. Plast Reconstr Surg. 1993; 91: 632-64.
4.      Bell E, Ehrlich HP, Buttle DJ, Nakatsuji T. Living tissue formed in vitro and accepted as skin-equivalent tissue of full-thickness. Science. 1981; 211:1052-1054.
5.      Heimbach D, Luterman A, Burke J, et al. Artificial dermis for major burns. Annals Surg. 1988; 208: 313-319.
6.      Matsuda K, Suzuki S, Isshiki K, et al. A bilayer "artificial skin" capable of sustained release of an antibiotic. Brit J Plast Surg. 1991; 44: 142-146.
7.      Cooper ML, Hansbrough JF. Use of a composite skin graft composed of cultured human keratinocytes and fibroblasts and a collagen-GAG matrix to cover full-thickness wounds on athymic mice. Surgery. 1991; 109: 198-207.
8.      Hansbrough JF, Morgan J, Greenleaf G. Evaluation of Graftskin composite grafts on full-thickness wounds on athymic mice. J Burn Care Rehabil. 1994; 15: 346-353.
9.      Hansbrough JF, Morgan J, Greenleaf G, Bartel R. Composite grafts of human keratinocytes grown on a polyglactin mesh-cultured fibroblast dermal substitute function as a bilayer skin replacement in full-thickness wounds on athymic mice. J Burn Care Rehabil. 1993; 14: 485-494.
10.  Matouskova E, Vogtova D, Konigova R. A recombined skin composed of human keratinocytes cultured on cell-free pig dermis. Burns.  1993; 19: 118-123.
11.  Takami Y, Matsuda T, Yoshitake M, Hanumadass M, Walter RJ. Dispase/detergent treated dermal matrix as a dermal substitute. Burns 1996; 22: 182-190.
12.  Loor MM, Truong A-T, Kowal-Vern, A, et al. Neovascularization during healing of wounds treated with dermal substitutes and fibrin glue in nude mice.  JACS. 2004; 199: S63.
13.  Loor MM, Truong A-T, Latenser BA, Wiley DE, Watler RJ. Healing and neovascularization of wounds implanted with dermal substitutes and fibrin glue in nude mice.  J Trauma.  2004; 57: 455.
14.  Teepe RGC, Kreis RW, Korbrugge EJ, et al. The use of cultured autologous epidermis in the treatment of extensive burn wounds. J Trauma. 1990; 30: 269-275.
15.  Nanchahal J, Ward CM. New grafts for old?  A review of alternatives to autologous skin. Brit J Plast Surg. 1992;  45: 354-363.
16.  Shakespeare P. Burn wound healing and skin substitutes. Burns. 2001;  27: 517-522.
17.  Kearney JN. Clinical evaluation of skin substitutes. Burns. 2001;  27: 545-551.
18.  Balasubramani M, Kumar TR, Babu M. Skin substitutes: a review. Burns.  2001;  27: 534-544.
19.  Boyce ST. Design principles for composition and performance of cultured skin substitutes. Burns. 2001;  27: 523-533.
20.  Rue LW, Cioffi WG, McManus WF, Pruitt BA. Wound closure and outcome in extensively burned patients treated with cultured autologous keratinocytes.  J Trauma.  1993; 34: 662-66.
21.  Gallico GG, O’Connor NE, Compton CC, Kehinde O, Green H.  Permanent coverage of large burn wounds with autologous cultured human epithelium.  NEJM. 1984; 311: 448-451.
22.  Cohen M, Bahoric A, Clarke HM. Aerosolization of epidermal cells with fibrin glue for the epithelialization of porcine wounds with unfavorable topography. Plast Reconstr Surg. 2001; 107: 1208-1215.
23.  Currie LJ, Martin R, Sharpe JR, James SE.  A comparison of keratinocyte cell sprays with and without fibrin glue.  Burns. 2003; 29: 677-685.
24.  Horch RE, Bannasch H, Kopp J, Andree C, Stark GB.  Single-cell suspensions of cultured human keratinocytes in fibrin glue reconstitute the epidermis.  Cell Transplant. 1998; 7: 309-317.
25.  Hunyadi J, Farkas B, Bertenyi C, Olah J, Dobozy A.  Keratinocyte grafting: a new means of transplantation for full-thickness wounds.  J Dermatol Surg Onc. 1988; 14: 75-78.
26.  Ronfard V, Rives J-M, Neveux Y, Carsin H, Barrandon Y.  Long-term regeneration of human epidermis on third degree burns transplanted with autologous cultured epithelium grown on a fibrin matrix.  Transplantation.  2000; 70: 1588-1598.
27.  Fraulin FOG, Bahoric DVM, Harrop AR, Hiruki T, Clarke HM.  Autotransplantation of epithelial cells in the pig via an aerosol vehicle.  J Burn Care Rehabil 1998; 19: 337-345.
28.  Navarro FA, Stoner ML, Lee HB, Park CS, Wood FM, Orgill DP. Melanocyte repopulation in full-thickness wounds using a cell spray apparatus. J Burn Care Rehabil. 2001; 22: 41-46.
29.  Navarro FA, Stoner ML, Park CS, Huertas JC, Lee HB, Wood FM, Orgill DP. Sprayed keratinocyte suspensions accelerate epidermal coverage in a porcine microwound model. J Burn Care Rehabil. 2000;. 21: 513-518.
30.  Jiao XY, Kopp J, Tanczos E, Voigt M, Stark GB.  Cultured keratinocytes suspended in fibrin glue to cover full-thickness wounds on athymic nude mice: comparison of two brands of fibrin glue.  Eur J Plast Surg. 1988; 21: 72-76.
31.  Chester DL, Balderson DS, Papini RPG.  A review of keratinocyte delivery to the wound bed.  J Burn Care Rehabil. 2004; 25: 266-275.
32.  Currie LJ, Sharpe JR, Martin R.  The use of fibrin glue in skin grafts and tissue-engineered skin replacements: a review.  Plast Reconstr Surg. 2001; 108: 1713-1726.
33.  Walter,RJ, Matsuda,T, Reyes,HM, Walter,JM, Hanumadass,M.  Characterization of acellular dermal matrices (ADMs) prepared by two different methods.  Burns 1998; 24: 104-113.
34.  Truong A-H, Kowal-Vern A, Latenser BA, Wiley DE, Walter RJ.  Comparison of dermal substitutes in wound healing utilizing a nude mouse model.  J Burns and Wounds. 2005; 4: 96-107.
35.  Dvorak HF, Brown LF, Detmar M, Dvorak AM.  Vascular permeability factor/vascular endothelial growth factor, microvascular hyperpermeability, and angiogenesis.  Am J Pathol. 1995; 146: 1029-1039.
36.  Li J, Zhang Y-P, Kirsner RS.  Angiogenesis in wound repair: angiogenic growth factors and the extracellular matrix.  Microsc Res Tech.  2003; 60: 107-114.
37.  Lingen MW.  Role of leukocytes and endothelial cells in the development of angiogenesis in inflammation and wound healing.  Arch Pathol Lab Med. 2001; 125: 67-71.
38.  Burke JF.  Observations on the development of an artificial skin: presidential address, 1982 American Burn Association Meeting. J Trauma. 1983; 23: 543-551.
39.  Moiemen NS, Staiano JJ, Ojeh, NO, Thway Y, Frame JD. Reconstructive surgery with a dermal regeneration template: clinical and histologic study.  Plast Reconstr Surg. 2001; 108: 93-103.
40.  Stern R, McPherson M, Longaker MT.  Histologic study of artificial skin used in the treatment of full-thickness thermal injury. J Burn Care Rehabil. 1990; 11: 7-13.
41.  Sheridan RL, Hegarty M, Tompkins RG, Burke JF.  Artificial skin in massive burns-results to ten years.  Eur J Plast Surg.  1994; 17: 91-93.
42.  Erdag G, Sheridan RL. Fibroblasts improve performance of cultured composite skin substitutes on athymic mice.  Burns. 2004; 30: 322-328.


FIGURES


 Figure 1. Percent of wound contraction over the 28-day study period for each of the dermal substitutes. Error bars represent SEM. Data was analyzed by one-way ANOVA with Tukey’s post tests.


Figure 2.  Laminin-stained cross-sections from the wound center following treatment with KC + FG only, Dermagraft, and Dermalogen on post-operative day 28 (above) and the corresponding gross appearance of these wounds at day 28 (below). Extensive vascularization is seen in both the superficial and deep dermis in all three of these wounds.Sutures mark the corners of the original wound.  Note the extensive contraction of wounds treated with KC + FG only and Dermalogen®.  Dermagraft®-implanted wounds showed poor epithelialization and poor incorporation into the wound with contraction limited only as long as the implant was retained.  Often part of the Dermagraft® implant underwent spontaneous dehiscence and was rejected from the wound. Magnification bar = 100 μm.


Figure 3.  Laminin-stained cross-sections from the wound center following treatment with AlloDerm, ADM, and Integra on post-operative day 28 (above) and the corresponding gross appearance of these wounds at day 28 (below). Controlled vessel ingrowth is seen in the AlloDerm and ADM groups. Note the numerous large and small cavities in the Integra® implant.  In life, these cavities held the collagen-chondroitin sulfate colloid that comprises Integra® and this colloid is still present at this time point. Several large vessels and vessels cut in tangential or longitudinal section are seen in this specimen.  The vessels appear to be growing around the cavities formed in the Integra implant.  In the gross photographs, sutures mark the corners of the original wound.  Note the limited contraction and nearly complete epithelialization of these wounds. Magnification bar = 100 μm.


  Figure 4.  Graph depicting changes in vessel number (mean±SEM) in the superficial dermis at the center of the wound over the study period of 28 days.  The dashed horizontal line represents the vascular counts in normal mouse skin (CTL). Note the hypovascularity of the Integra, AlloDerm, ADM, and Dermalogen groups at day 14 in comparison to CTL, and the hypervascularity seen with implanted Dermagraft at day 28. Data were analyzed using one-way ANOVA with Tukey’s post tests.
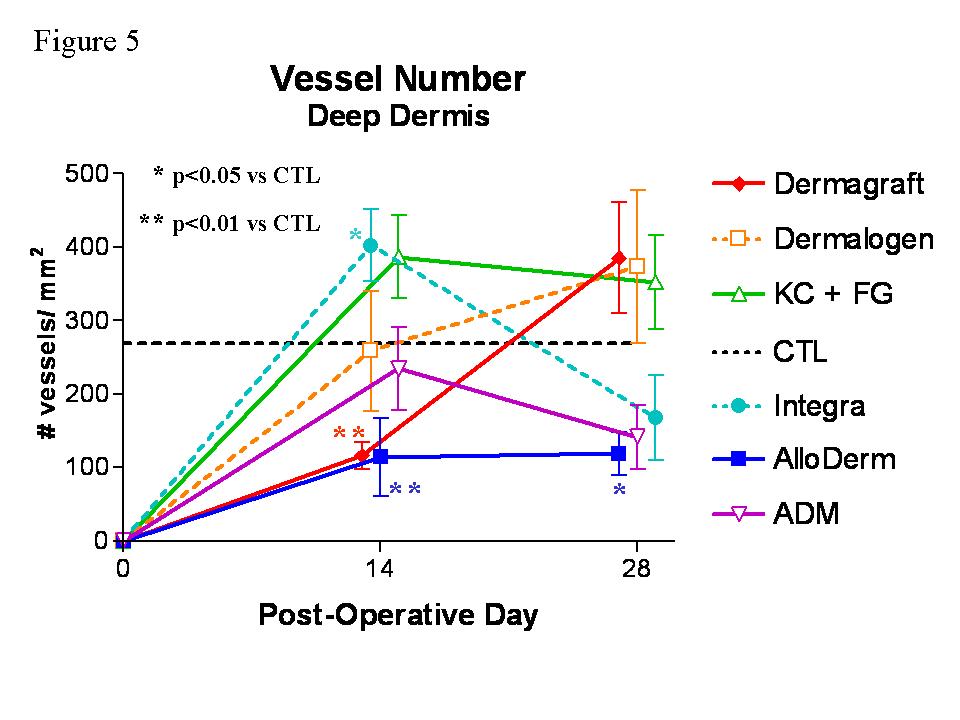

Figure 5.  Graph depicting changes in vessel number (mean±SEM) in the deep dermis at the center of the wound over the study period of 28 days.  The horizontal dashed line represents the vascular counts in normal mouse skin (CTL). Data were analyzed using one-way ANOVA with Tukey’s post tests.


Figure 6.  Graph depicting changes in vessel areas (mean±SEM) in the superficial dermis at the center of the wound over the study period of 28 days.  The dashed horizontal line represents the vessel size in normal mouse skin (CTL). Note that the vessels in wounds treated with Integra are larger than CTL at day 14 (p<0.001) and day 28 (p<0.01).  Data were analyzed using one-way ANOVA with Tukey’s post tests.


   Figure 7.  Graph depicting changes in vessel areas (mean±SEM) in the deep dermis at the center of the wound over the study period of 28 days.  The dashed horizontal line represents the vessel size in normal mouse skin (CTL). Note that the vessels in wounds treated with Integra are larger than CTL at day 14 (p<0.001) and day 28 (p<0.01).  Data were analyzed using one-way ANOVA with Tukey’s post tests.


Figure 8.  Graph depicting percentage of original wound area epithelialized over the study period of 28 days.  Error bars represent SEM.  At day 28, wounds implanted with AlloDerm, Integra, or ADM were approximately 40% reepithelialized, whereas wounds implanted with Dermagraft or Dermalogen were only 10-20% reepithelialized. 
Table 1.  Table of vessel numbers and sizes (mean±SEM) in the total dermis (superficial + deep) for each of the groups at day 28.

FYI.  The content on this blog is copyright protected by the author.  Feel free to read, copy, and disseminate the studies described here, but please indicate the origin of the work by citing this blog URL as an electronic web citation when it is appropriate to recognize and attribute the work of others.

Formylpeptide Chemoattractant Binding Sites in Ileum


April 14, 2012 

After we developed a method for detecting formylpeptide chemotaxis receptors using autoradiography, we adapted this method to examine these binding sites or receptors in gut tissue.  We exposed freshly harvested segments of guinea pig ileum to iodinated formylhexapeptide, fixed and processed the tissue histologically, and then did autoradiography to localize the radiolabeled peptide in the tissue sections.

Formylpeptide chemoattractants are known to be capable of eliciting contraction of smooth muscle in guinea pig ileum but the cellular target of interaction between peptide and ileum is unknown.  This suggests that receptors specific for formylpeptides may be found on cells in the ileum and may be responsible for ileal smooth muscle contraction.  Formylpeptides may bind directly to ileal smooth muscle and thereby elicit its contraction.  Alternatively, they may act on smooth muscle indirectly by first binding to and stimulating enteric nerves or activating inflammatory cells (macrophages, polymorphonuclear leukocytes, lymphocytes).  Secondary to this, soluble mediators such as neurotransmitters (eg., acetylcholine, substance P) or arachidonate metabolites may be released resulting in smooth muscle contraction.

This study was performed to localize the sites of formylpeptide binding in guinea pig ileum.  Using iodinated formylhexapeptide in conjunction with light microscope autoradiography of sectioned ileum, it appears that formylpeptide binds specifically and in relatively large amounts directly to ileal smooth muscle (muscularis externa and muscularis mucosa).  However, very little receptor-mediated binding to enteric nerve plexuses, lamina propria, infiltrating leukocytes, or ileal epithelium was observed.  

Since formylpeptides are produced in prodigious quantities by bacteria, the release of these peptides in or around the gut may trigger increased smooth muscle contractility.  This may promote both normal gut motility and the augmented motility associated with enteric infections.

 Below is the full text of this paper and a link to the paper in PDF format.

 Formylpeptide Chemoattractant Binding in Ileum


Localization of Formylpeptide Chemoattractant Binding Sites

in Guinea Pig Ileum

by

Robert J.  Walter*
Department of Anatomy
University of Illinois at Chicago
Chicago, IL 60612

Wayne A.  Marasco
Department of Pathology
University of Michigan Medical School
Ann Arbor, MI


Running Head: Formylpeptide Binding in Guinea Pig Ileum
Keywords - formylpeptide, chemoattractant, chemotaxis, smooth muscle, ileum, contractility, receptors, bacterial peptides.

 * To whom reprint requests should be addressed:

Robert J.  Walter, Ph.D.
Department of Anatomy m/c 512
University of Illinois at Chicago
P.O.  Box 6998
Chicago, IL 60680

312/996-9464


ABSTRACT

Formylpeptide chemoattractants are known to be capable of eliciting contraction of smooth muscle in guinea pig ileum but the cellular target of interaction between peptide and ileum is unknown.  To directly ascertain sites for binding and uptake of formylpeptide, we have exposed segments of guinea pig ileum to N-formyl-norleucyl-leucyl-phenylalanyl-norleucyl-I125-tyrosyl-lysine (10 nM), at either 4ºC or 37ºC.  After this initial incubation, the tissue was rinsed in buffer, fixed, embedded, sectioned (at 3 µm thickness), and autoradiographed.  Developed autoradiographs were examined and silver grains associated with different regions of ileum quantitated.  At both temperatures the smooth muscle layers (outer longitudinal muscle, inner circular muscle, and muscularis mucosa) were heavily labeled with silver grains.  Very few grains were found to be associated with the epithelial cells of the intestinal villi.  At 4ºC, very few grains were observed overlying enteric nerve plexuses, whereas these structures were heavily labeled in ileum exposed to I125-hexapeptide at 37ºC.  In control experiments performed at 4ºC where iodinated and excess unlabeled hexapeptide were added simultaneously, labeling was markedly reduced in all regions of ileum. 

            Similarly, in control experiments performed at 37ºC, labeling was also reduced but not to the same extent as that observed at 4ºC.  We conclude from these studies that formylhexapeptide chemoattractants bind specifically and in large amounts to receptors on ileal smooth muscle but not to enteric nerve plexuses.  As demonstrated previously, this binding is receptor-mediated and may directly induce ileal smooth muscle contraction.  The occurrence of such binding sites on ileal smooth muscle may promote both normal gut motility and the augmented motility associated with enteric infections.


Keywords - formylpeptide, chemoattractant, chemotaxis, smooth muscle, ileum, contractility, receptors, bacterial peptides.


INTRODUCTION

            There are several classes of compounds that elicit potent secretory and chemotactic responses from normal polymorphonuclear (PMN) and mononuclear leukocytes.  Of these, the formylmethionylpeptides and the complement cleavage products are by far the most fully characterized.  The formylpeptides are a group of low molecular weight oligopeptides found in bacteria (Snyderman and Pike, 1984a, b) and mitochondria (Carp, 1982).  Purified synthetic analogs of these naturally occurring substances have been synthesized and their leukotactic activities characterized (Snyderman and Pike, 1984a, b; Marasco et al., 1984; Miyake et al., 1983).  C5a, a fragment of the fifth component of complement, is the major source of chemotactic activity found in serum (Snyderman et al., 1971).

In leukocytes, the responses elicited by both classes of chemoattractant compounds are known to be mediated by cell surface receptors specific for each class of attractant.  Furthermore, both types of chemoattractants have been shown to be capable of initiating the contraction of smooth muscle and are potent spasmogenic agents in both guinea pig ileum and lung (Rocha e Silva et al., 1951; Stimler et al., 1981; Regal and Pickering, 1981; Hamel et al., 1984).  The structure-activity relationships (i.e., relative potencies) for a series of related, synthetic N-formylpeptides in initiating ileal smooth muscle contraction are very similar to those seen for leukocyte chemotaxis.  In addition, the competitive formylpeptide receptor antagonist, Boc-Phe-Leu-Phe-Leu-Phe inhibited the ileal contractile response to formylpeptide (Marasco et al., 1982).  This suggests that receptors specific for formylpeptides may be found on cells in the ileum and may be responsible for ileal smooth muscle contraction.  However, formylpeptide binding to these receptors may directly or indirectly elicit smooth muscle contraction.  Formylpeptides may bind directly to ileal smooth muscle and thereby elicit its contraction.  Alternatively, they may act on smooth muscle indirectly by first binding to and stimulating enteric nerves or activating inflammatory cells (macrophages, polymorphonuclear leukocytes, lymphocytes).  Secondary to this, soluble mediators such as neurotransmitters (eg., acetylcholine, substance P) or arachidonate metabolites may be released resulting in smooth muscle contraction.

This study was performed to localize the sites of formylpeptide binding in guinea pig ileum.  Using iodinated formylhexapeptide in conjunction with light microscope autoradiography of sectioned ileum, it appears that formylpeptide binds specifically and in relatively large amounts directly to ileal smooth muscle (muscularis externa and muscularis mucosa).  However, very little receptor-mediated binding to enteric nerve plexuses, lamina propria, infiltrating leukocytes, or ileal epithelium was observed.


METHODS AND MATERIALS

Tissue Isolation

Adult male guinea pigs were anesthetized with ether and 3 cm of terminal ileum isolated and flushed several times with cold Krebs solution (130 mM NaCl, 4.7 mM KCl, 1.18 mM KH2PO4, 1.17 mM MgSO4.7H2O, 1.6 mM CaCl2, 14.9 mM NaHCO3, 5.5 mM dextrose, 2 mg/ml bovine serum albumin).  The isolated ileum was cut into 2 mm long pieces, suspended in Krebs solution and allowed to equilibrate for 60 min at 37ºC in an atmosphere of 5% CO2 / 95% air with several changes of buffer. 

Hexapeptide Binding Conditions

N-formyl-norleucyl-leucyl-phenylalanyl-norleucyl-tyrosyl-lysine (Peninsula Laboratories, Belmont, CA) was iodinated by the chloramine-T method using carrier-free I125 as described previously (Marasco et al., 1985a: Jesaitis et al., 1983, 1984).  After equilibration in Krebs buffer at 37ºC, segments of ileum were exposed to 10 nM I125-hexapeptide at 4ºC or 37ºC for either 3 or 30 min.  Excess (500-fold) unlabeled hexapeptide was added simultaneously with I125-hexapeptide to one group of tissue samples so that they might serve as controls for nonspecific hexapeptide binding.  It should be noted that buffer containing formylhexapeptide was in contact with both the serosal and luminal aspects as well as the cut ends of each ileal segment providing a large surface area for entry of this peptide into each segment.

Upon completion of this incubation, ileal segments were rinsed thoroughly in two changes of Krebs solution (4ºC) containing 2 mg/ml bovine serum albumin and a final wash in Krebs solution lacking albumin.  This washing was accomplished in 60 seconds whereupon ileal segments were promptly fixed in 2% glutaraldehyde, 1% paraformaldehyde, 0.1 M cacodylate, pH 7.4 for 18 hours at 4ºC. 

Tissue Preparation and Autoradiography

Fixed ileal segments were rinsed in cacodylate buffer (0.1 M) and dehydrated in graded ethanol series.  Tissue was then embedded in glycol methacrylate (DuPont Instruments, Newtown, CT) and each tissue block trimmed to a depth of approximately 0.5 mm before sectioning was commenced.  Cross-sections of ileum were then cut at 3 µm thickness and sections mounted on acid-cleaned, subbed glass slides.  Slides with adherent sections were then dipped in Kodak NTB-2 emulsion (diluted 1:3 with distilled water), air dried, and stored for 14 days in the dark at 4ºC.  Exposed autoradiographs were developed using Kodak D-19, fixed, stained with 0.1% cresyl violet, and coverglasses mounted using Permount. 

Specimens were examined and photographed using a Nikon Optiphot microscope equipped with an Olympus OM-2n camera.  Bright-field optics were used to identify the specific regions of interest and dark-field optics used to visualize and count silver grains associated with these regions.  Silver grains were counted using an eyepiece reticle at 100X magnification.  The reticle grid divided the field into 27 by 27 µm squares.  Grains within 10 such squares overlying each of the regions of interest were then counted.  The regions examined included: muscularis externa, both outer longitudinal and inner circular layers; submucosa; muscularis mucosa; epithelial cells (villi and crypts); and the lumen.  Three separate experiments were performed, the data from these experiments combined, and the mean number of grains/test area ± S.E.M calculated.


RESULTS

Background and Specificity of Labeling

The emulsion background seen over the lumen was very low (usually less than 1 grain per unit test area = 729 µm2) and only a small percentage (less than 5%) of the total amount of binding seen in the muscle layers (Table 1).  Ileal segments exposed to I125-hexapeptide in the presence of excess unlabeled hexapeptide exhibited some non-specific binding of labeled hexapeptide within the ileum (3-4 grains/ 729 µm2).  However, in the muscle layers of the ileum a high degree of specific labeling, 3 to 5 times as many specific as non-specific grains, was evident.

The non-specific binding observed in these experiments could be reduced considerably by extending the time of washing after the initial formylpeptide binding (data not shown) but the total amount of specific labeling was also greatly reduced.  Thus, the background labeling probably results from residual unbound I125-hexapeptide not removed during the washing procedure.  However, since hexapeptide binding to the leukocyte formylpeptide receptor is known to be highly reversible (Sklar et al., 1984) longer washings might remove significant amounts of receptor-bound I125-hexapeptide.  As a result a tissue background level of 3-4 grains per test area was tolerated in order to maintain maximal specific binding of hexapeptide.

The amount of non-specific labeling seen in ileal segments exposed to I125-hexapeptide at 37ºC was much higher than that seen at 4ºC (Table 2).  At low temperatures, labeling is due primarily to specific receptor-mediated binding of formylhexapeptide to the cell surface.  Although not significant at 4ºC, fluid-phase endocytosis becomes a major route of internalization at 37ºC.  Thus, 5 to 15 grains/ 729 µm2 were seen over the smooth muscle layers at 37ºC even in the presence of excess unlabeled hexapeptide.  Much of this labeling is probably due to a combination of fluid-phase and receptor-mediated endocytosis of I125-hexapeptide.

Localization of Hexapeptide Binding

The amount of specific binding increased markedly (50-100%) in samples of tissue exposed to I125-hexapeptide for 30 min at 4ºC as compared to 3 min at 4ºC (Figures 1 and 2).  This reflects a move towards equilibrium binding.  However, a greater increase in binding occurred in deeper layers of the ileum than in the superficial layers (46%, 67%, and 106% in the outer longitudinal, inner circular, and muscularis mucosa, respectively) after 30 minutes.  Thus, the tissue mass or intercellular junctions evidently created a significant barrier to the diffusion and binding of formylpeptide at the early time point.  Nevertheless, labeled hexapeptide had penetrated the deepest layers (i.e., muscularis mucosa and submucosa) within three minutes and had bound extensively in all muscle layers within 30 minutes.  Non-specific binding was not significantly different at these two incubation times. 

I125-labeled formylpeptide was localized primarily over the longitudinal and circular smooth muscle layers as well as the muscularis mucosa.  The labeling seen associated with smooth muscle was associated primarily with the cell surface rather than intracellular organelles or cytoplasm (Figure 3 A-D).  Little or no specific binding was found over the submucosa or ileal epithelial cells.  PMN, eosinophils, lymphocytes, and tissue macrophages were seen occasionally in the lamina propria and blood vessels, but very little binding was seen compared to that observed on smooth muscle (Figure 3 E,F).  Furthermore, very little binding to Auerbach`s or Meissner`s plexuses was observed at 4ºC (see Figure 1 at arrows) and very few grains were associated with smooth muscle in blood vessel walls.

The amount of label seen in tissue exposed to I125-hexapeptide at 37ºC was increased compared to that seen in parallel incubations at 4ºC (Table 2).  Labeling was increased up to 150% in tissue samples exposed to iodinated hexapeptide for 30 min as compared to 3 min at 37ºC.  Non-specific labeling (Figures 4 and 5) was considerably higher at 37ºC than at 4ºC and comprised a large portion (50-80 % in the muscularis externa) of the total labeling observed at 37ºC.  Specific labeling was seen in ileal smooth muscle layers (muscularis externa and muscularis mucosa) but far less label was associated with the epithelial cell layer.  At 37ºC, large amounts of label were associated with Auerbach`s and Meissner`s nerve plexuses (see Figures 4 and 5).  This labeling was not reduced in the presence of excess unlabeled hexapeptide and was thus considered to be the result of fluid-phase endocytosis of I125-hexapeptide.  Samples of terminal guinea pig ileum exposed to hexapeptide at 37ºC also contracted in response to the binding or uptake of formylpeptide as described previously by Marasco et al.  (1982).


DISCUSSION

This study shows that iodinated formylhexapeptide binds primarily to the outer longitudinal and inner circular muscle layers and the muscularis mucosa of the guinea pig ileum.  Binding appears to be specific for smooth muscle in these layers since even neighboring vascular smooth muscle does not bind formylpeptide.  In addition,formylpeptide exhibits little or no specific binding to absorptive or secretory cells found in the intestinal epithelium.  Very little specific binding to infiltrating leukocytes or intravascular leukocytes was detected under the conditions employed for these experiments.  Thus, the possibility that formylpeptides may induce the release of soluble mediators of ileal contraction from leukocytes seems remote.  This relative paucity of binding also suggests that the numbers or binding affinities of formylpeptide receptors present on the smooth muscle cells may be higher than those on leukocytes.  Alternatively, the formylpeptide receptors of infiltrating leukocytes may be blocked or down-regulated due to local, endogenous factors.

Marasco et al. (1982) found formylpeptides to be potent spasmogenic agents for guinea pig ileum.  However the response (eg., contour of dose-response curves, latency period, tachyphylaxis) of ileum to these peptides differed significantly from that of ileum to substance P or histamine.  This suggests that formylpeptides and structurally-related neuropeptides such as substance P may interact with the ileum by way of distinctly different mechanisms.  The occurrence and physiologic activities of substance P as well as tissue distribution of substance P receptors have been characterized in considerable detail (Souquet et al., 1985; Regoli et al., 1984; Costa et al., 1982; Holzer and Petsche, 1983).  Substance P receptors have been demonstrated on ileal smooth muscle as well as enteric nerve plexuses (Costa et al., 1982).  The effects of substance P on smooth muscle contraction are thought to be mediated by endogenous agents such as acetylcholine, prostaglandins, or histamine. 

On the other hand, we have found that iodinated formylpeptide binds with great specificity to smooth muscle but does not bind to enteric nerve plexuses at 4ºC.  At 37ºC, however, formylpeptide is taken up by these plexuses in large amounts.  It is possible that this internalized peptide may elicit subsequent effects on ileal smooth muscle innervated by these nerves but there is no direct evidence that this does occur.  However, the absence of receptor sites specific for formylpeptide on these plexuses (as seen at 4ºC) would argue against such a mechanism.  Substances internalized by bulk fluid pinocytosis are generally targeted for lysosomal destruction (Farquhar, 1983; DeDuve and Wattiaux, 1966) and are therefore not likely to evoke rapid, specific cellular responses of the sort typified by cell surface receptor-mediated phenomena.  The occurrence of very abundant cell surface receptors specific for formylpeptide on cells in the smooth muscle layers indicates that these peptides may exert a direct effect on smooth muscle in these regions.

Normally, resident intestinal flora continually produce and release small quantities of formylpeptides into the gut lumen (Marasco et al., 1984; Miyake et al., 1983).  Magnusson et al.  (1985) have demonstrated that formylpeptides infused intraluminally greatly increase the permeability of ileal epithelia for low molecular weight substances.  Under physiological conditions, this may allow bacterial formylpeptides to penetrate the epithelium more readily and bind directly to ileal smooth muscle.  This would then result in increased smooth muscle contraction and perhaps help to maintain the normal motility of the gut.  The observation that germ-free mice exhibit greatly reduced transit of intraluminal radiotracers lends further credulity to this hypothesis (Abrams and Bishop, 1967).  Under certain pathological conditions involving the gut such as enteric bacterial infections, peristaltic rates and smooth muscle contraction are often dramatically increased.  Under these circumstances, large quantities of bacterial formylpeptides may be elaborated and released into the gut lumen.  These peptides may then penetrate into the muscular layers of the gut and act there to vastly augment the usual contractility of intestinal smooth muscle. 

From this data and other studies, we conclude that synthetic formylpeptides can increase the permeability of the intestinal epithelium, penetrate that epithelium, bind to ileal smooth muscle, and elicit increased smooth muscle contraction.  Since these formylpeptides are synthetic analogs of naturally occurring bacterial peptides, we speculate that intraluminal bacteria may release similar factors that subsequently affect intestinal contractility. 


TABLE I

Silver Grains Associated with Guinea Pig Ileum after Exposure to

I125-Hexapeptide at 4ºC


Layer of Ileum                               I125-Hexapeptide                      I125-Hexapeptide
+ Unlabeled Hexapeptide
                                                3 min                30 min              3 min                30 min
______________________________________________________________________

Muscle
 Outer longitudinal                     10.8 ± 1.6*      15.8 ±1.4**     3.0 ±0.5           3.2 ±0.6
       
 Inner circular                           11.0 ±1.2**     20.1 ±1.3**     3.0 ±0.5           3.5 ±0.8

Submucosa                               4.0 ±1.3           6.7 ±1.5           3.7 ±0.5           4.2 ±0.7

Muscularis mucosa                   8.0 ±1.4**       16.5 ±1.8*       3.7 ±0.6           4.2 ±0.7

Epithelial cells
 (Villi and crypts)                      2.0 ±0.5           2.2 ±0.5           0.7 ±0.3           1.0 ±0.3

Lumen                                      0.7 ±0.3           1.0 ±0.2           0.7 ±0.3           0.8 ±0.3
______________________________________________________________________

2 mm segments of ileum exposed to 10 nM I125-hexapeptide in Krebs buffer at 4ºC, rinsed rapidly through 3 changes of Krebs buffer at 4ºC and then fixed in 2% glutaraldehyde with 1% paraformaldehyde in 0.1 M cacodylate buffer, pH 7.4 overnight.  To control for nonspecific binding, tissue was exposed to 10 nM I125-hexapeptide containing 5 µM unlabeled hexapeptide.

Tissue was dehydrated in ethanol series, embedded in glycol methacrylate, cut into 3 µm thick sections, coated with Kodak NTB-2 emulsion, and exposed in the dark at 4ºC for 14 days.  Autoradiographs were developed in Kodak D-19, stained in cresyl violet, and mounted in Permount.

Silver grains were counted using a reticle at 100X magnification.  Grains within a 27 by 27 µm square were counted overlying each of the regions designated above and 10 squares were counted for each region.  Three separate experiments were performed.  Each entry represents the mean ± SEM for three experiments.

Grain counts for I125-hexapeptide compared to I125-hexapeptide + excess unlabeled hexapeptide at equivalent times using 2-tailed t-test; * p < 0.03 ; ** p < 0.005


TABLE II

Silver Grains Associated with Guinea Pig Ileum after Exposure to

I125-Hexapeptide at 37ºC


Layer of Ileum                              I125-Hexapeptide                      I125-Hexapeptide +
                                                                                                Unlabeled Hexapeptide
                                                3 min                30 min              3 min                30 min
______________________________________________________________________

Muscle
 Outer longitudinal                     16.2 ± 2.1        23.0 ± 2.8*      5.0 ± 1.1          11.5 ± 2.5
       
 Inner circular                           9.7 ± 1.3          21.2 ± 3.1        8.0 ± 2.8          15.5 ± 3.3

Submucosa                               4.2 ± 1.0          5.0 ± 1.5          6.0 ± 2.2           7.7 ± 2.1

Muscularis mucosa                   8.0 ± 1.5          20.2 ± 3.7        7.2 ± 1.8          10.5 ± 2.6

Epithelial cells
 (Villi and crypts)                      3.0 ± 0.5          5.0 ± 0.3          2.5 ± 0.5          4.0 ± 1.0

Lumen                                      0.7 ± 0.3          0.5 ± 0.2          1.0 ± 0.3          1.1 ± 0.4 ______________________________________________________________________

2 mm segments of ileum exposed to 10 nM I125-hexapeptide in Krebs buffer at 37ºC, rinsed rapidly through 3 changes of Krebs buffer at 4ºC and then fixed in 2% glutaraldehyde with 1% paraformaldehyde in 0.1 M cacodylate buffer, pH 7.4 overnight.  To control for nonspecific binding, tissue was exposed to 10 nM I125-hexapeptide containing 5 µM unlabeled hexapeptide.

Tissue was dehydrated in ethanol series, embedded in glycol methacrylate, cut into 3 µm thick sections, coated with Kodak NTB-2 emulsion, and exposed in the dark at 4ºC for 14 days.  Autoradiographs were developed in Kodak D-19, stained in cresyl violet, and mounted in Permount.

Silver grains were counted using a reticle at 100X magnification.  Grains within a 27 by 27 µm square were counted overlying each of the regions designated above and 10 squares were counted for each region.  Three separate experiments were performed.  Each entry represents the mean
SEM for three experiments.

Grain counts for I125-hexapeptide compared to I125-hexapeptide + excess unlabeled hexapeptide at equivalent times using 2-tailed t-test; * p < 0.04


REFERENCES

ABRAMS, G.D.  and BISHOP, J.E.  1967.  Effect of normal microbial flora on gastrointestinal motility.  Proc.  Soc.  Exp.  Biol.  Med.  126: 301-304.

ASWANIKUMAR, S., CORCORAN, B., SCHIFFMAN, E., DAY, A.R., FREER, R.J.,
SHOWELL, H.J., and PERT, C.B.  1977.  Demonstration of a receptor on rabbit neutrophils for chemotactic peptides.  Biochem.  Biophys.  Res.  Commun.  74: 810-825.

BECKER, E.L.  AND MARASCO, W.A.  1985.  Chemotaxis and activation of neutrophils.  In "Symposium on Chemical Mediators of Inflammation".  Cohen, S., Hayashi, H., Saito, K., and Takado, A., eds.  Academic Press (in press).

CARP, H.  1982.  Mitochondrial N-formyl methionyl proteins as chemoattractants for neutrophils.  J.  Exp.  Med.  155: 264-273.

COSTA, M., FURNESS, J.B., FRANCO, R., LLEWELLYN-SMITH, I., MURPHY, R., and
BEARDSLEY, A.M.  1982.  Substance P in nerve tissue in the gut.  in, "Substance P in the Nervous System", Porter, R.  and O`Connor, M.  (eds.), London, Pitman Books Ltd.  pp.  129-144.

DEDUVE, C.  and WATTIAUX, R.  1966.  Function of lysosomes.  Annu.  Rev. Physiol.  28:435-492.

FARQUHAR, M.G.  1983.  Multiple pathways of exocytosis, endocytosis, and membrane recycling: validation of a Golgi route.  Fed.  Proc.  42:2407-2413.

FERTUCK, H.C.  and SALPETER, M.M.  1974.  Sensitivity in electron microscope autoradiography for I-125.  J.  Histochem.  Cytochem.  22: 80-87.

GALLIN, J.I., SELIGMANN, B.E., and FLETCHER, M.P.  1983.  Dynamics of human neutrophil receptors for the chemoattractant fmet-leu-phe.  Agents Actions Suppl.) 12: 290-308.

HAMEL, R., FORD-HUTCHINSON, A.W., LORD, A, and CIRINO, M.  1984.  Bronchoconstriction induced by N-formyl-methionyl-leucyl-phenylalanine in the guinea pig: involvement of arachidonic acid metabolites.  Prostaglandins 28: 43-56.

HOLZER, P.  and PETSCHE, U.  1983.  On the mechanism of contraction and desensitization induced by substance P in the intestinal muscle in the guinea-pig.  J.  Physiol.  342:549-568.

MAGNUSSON, K.-E., DAHLGREN, C., and SJOLANDER, A.  1985.  Effect of N-formylated methionyl-phenylalanine (FMP) and methionyl-leucyl-phenylalanine (FMLP) on gut permeability.  Inflammation 9:365-373.

MARASCO, W.A., BECKER, K.A., FELTNER, D.E., BROWN, C.S., WARD, P.A.  and
NAIRN, R.  1985.  Covalent affinity labeling, detergent solubilization, and fluid-phase characterization of the rabbit neutrophil formyl peptide chemotaxis receptor.  Biochem.  24: 2227-2236.

MARASCO, W.A., FANTONE, J.C., and WARD, P.A.  1982.  Spasmogenic activity of
chemotactic N-formylated oligopeptides: Identity of structure-function relationships for chemotactic and spasmogenic activities.  Proc.  Nat.  Acad.  Sci.  USA 79:7470-7473.

MARASCO, W.A., PHAN, S.H., KRUTZSCH, H., SHOWELL, H.J., FELTNER, D.E.,
NAIRN, R., BECKER, E.L., and WARD, P.A.  1984.  Purification and identification of formyl-methionyl-leucyl-phenylalanine as the major peptide neutrophil chemotactic factor produced by Escherichia coli.  J.  Biol.  Chem.  259: 5430-5439.

MIYAKE, Y., TADASHI, Y., KAZUHIRO, F., SUGINAKA, H., NAKAJIMA, T., and
MORIYAMA, T.  1983.  Purification and characterization of neutrophil chemotactic factors of Streptococcus sanguis.  Biochimica Biophysica Acta 758: 181-186.

NIEDEL, J.E.  and CUATRECASAS, P.  1980.  Formyl peptide chemotactic receptors of leukocytes and macrophages.  Curr.  Top.  Cell.  Regul.  17: 137-170.

NIEDEL, J., WILKINSON, S., AND CUATRACASAS, P.  1979.  Receptor-mediated uptake of I-125-chemotactic peptide by human neutrophils.  J.  Biol.  Chem.  254: 10700-10708.

REGAL, J.F.  and PICKERING, R.J.  1981.  C5a and antigen-induced tracheal contraction: effect of a combination of an antihistamine and cyclo-oxygenase inhibitors.  J.  Immunol.  126: 313-316.

ROCHA DE SILVA, M., BIER, O., and ARONSON, M.  1951.  Histamine release by anaphylatoxin.  Nature (London) 168: 465-466.

SALPETER, M.M., FERTUCK, H.C., and SALPETER, E.E.  1977.  Resolution in electron microscope autoradiography.  III.  Iodine-125, the effect of heavy metal staining, and a reassessment of critical parameters.  J.  Cell Biol.  72: 161-173.

SCHIFFMAN, E.  and GALLIN, J.I.  1979.  Biochemistry of phagocyte chemotaxis.  Curr.  Top.  Cell.  Regul.  15: 203-261.

SKLAR, L.A., FINNEY, D.A., OATES, Z.G., JESAITIS, A.J., PAINTER, R.G., and COCHRANE, C.G.  1984.  The dynamics of ligand-receptor interactions.  Real-time analysis of dissociation, and internalization of an N-formyl peptide and its receptors on the human neutrophil.  J.  Biol.  Chem.  259:5661-5669.

SNYDERMAN, R., PHILLIPS, J.K., and MERGENHAGEN, S.E.  1971.  Biological activity of complement in vivo: Role of C5 in the accumulation of polymorphonuclear leukocytes in inflammatory exudates.  J.  Exp.  Med.  134:1131-1143.

SNYDERMAN, R.  and PIKE, M.C.  1984a.  Chemoattractant receptors on phagocytic cells.  Ann.  Rev.  Immunol.  2: 257-281.

SNYDERMAN, R.  and PIKE, M.C.  1984b.  Transductional mechanisms of chemoattractant receptors on leukocytes.  Contemp.  Top.  Immunobiol.  14: 1-28.

SOUQUET, J.C., GRIDER, J.R., BITAR, K.N., and MAKLOUF, G.M.  1985.  Receptors for mammalian tachykinins on isolated intestinal smooth muscle cells.  Am.  J.  Physiol.  249:G533-G538.

STIMLER, N.P., BROCKLEHURST, W.E., BLOOR, C.M., and HUGLI, T.E.  1981. 
Anaphylatoxin-mediated contraction of guinea pig lung strips: a nonhistamine tissue response.  J.  Immunol.  126: 2258-2261.

WALTER, R.J.  and MARASCO, W.A.  1984.  Localization of chemotactic peptide receptors on rabbit neutrophils.  Exp.  Cell Res.  154: 613-618.

WILLIAMS, L.T., SNYDERMAN, R., PIKE, M.C., AND LEFKOWITZ, R.J.  1977.  Specific receptor sites for chemotactic peptides on human polymorphonuclear leukocytes.  Proc.  Nat.  Acad.  Sci.  USA 74: 1204-1208.


 FIGURES


 Figure 1.  Guinea pig ileum exposed to 10 nM I125-hexapeptide at 4ºC for 3 min, washed for 1 min in Krebs solution, and then fixed.  Bright-field images of ileal cross-sections (3µm thick) are seen in the left column and corresponding dark-field images in the right.  Many silver grains are seen overlying both layers of the muscularis externa (A,B), both outer longitudinal muscle (olm) and inner circular muscle (icm).  In addition, a number of grains are also seen over the muscularis mucosa (mm).  Auerbach`s plexus (indicated by arrows) is virtually without associated silver grains except at its very periphery.  Very few grains are seen associated with the epithelial cells of the ileum (C,D) and even fewer in the lumen.  Control tissue exposed simultaneously to 10 nM iodinated hexapeptide and 5 µM unlabeled hexapeptide (E,F) shows a great reduction in the number of silver grains.  Magnification bar = 100 µm.


 Figure 2.  Guinea pig ileum exposed to 10 nM I125-hexapeptide at 4ºC for 30 min, rinsed in Krebs solution at 4ºC for 1 min, and then fixed.  Three micrometer thick cross-sections of ileum (bright-field, left column; corresponding dark-field, right column) show many silver grains (A,B) associated with the outer longitudinal and inner circular muscle layers (olm and icm, respectively) and also with the muscularis mucosa (mm).  Very few grains are seen in association with the lamina propria or with the epithelial cell layer (C,D).

Under similar conditions, ileal segments exposed to iodinated hexapeptide simultaneously with excess (500-fold) unlabeled hexapeptide show comparatively very few grains overlying the smooth muscle layers (E,F).  An unlabeled Auerbach`s plexus is also seen (arrow).  Magnification bar = 100 µm.


Figure 3.  Ileum initially exposed to I125-hexapeptide for 30 min at 4ºC, rinsed, fixed, and cross-sectioned.  At high magnification, cells in both the outer longitudinal (A,B) and inner circular (C, D) muscle layers exhibit silver grains localized on the muscle plasma membrane.  Perivascular tissue macrophage found in the lamina propria (E, F) displays prominent granular cytoplasmic inclusions (dense by bright-field and refractile by dark-field) but no silver grains indicating a lack of I125-hexapeptide binding.  Magnification bar = 15 µm.


Figure 4.  Guinea pig ileum exposed to 10 nM I125-hexapeptide for 3 min at 37ºC, rinsed in Krebs solution for 1 min at 4ºC, and then fixed.  Cross-sectioned ileum (bright-field, left column; corresponding dark-field, right column) shows a great many silver grains (A,B) overlying the outer longitudinal muscle (olm) as well as the inner circular muscle (icm) layers.  In addition, many grains are seen overlying the Auerbach`s plexus (arrow) beneath the outer longitudinal muscle layer.  Few grains are seen overlying the epithelial cells and very few over the lumen (C,D).

Ileal segments exposed simultaneously to iodinated and excess unlabeled hexapeptide for 3 min at 37ºC display considerable numbers of silver grains associated with the muscularis externa (E,F).  Magnification bar = 100 µm.
 Figure 5.  Segments of guinea pig ileum exposed to I125-hexapeptide for 30 min at 37ºC, rinsed in Krebs solution for 1 min at 4ºC, and then fixed.  Cross-sectioned ileum (bright-field, left column; corresponding dark-field, right column) display large numbers of grains over the muscularis externa (outer longitudinal and inner circular layers; olm and icm, respectively), muscularis mucosa (mm), and Auerbach`s plexus (arrow) (A,B).  Increased numbers of grains are also seen associated with the epithelial layer (C,D).  Furthermore, ileal segments exposed simultaneously to labeled and excess unlabeled hexapeptide at 37ºC for 30 min (E,F) also exhibited relatively large numbers of silver grains over the smooth muscle layers of the ileum.  Magnification bar = 100 µm.


 FYI.  The content on this blog is copyright protected © by the author.  Feel free to read, copy, and disseminate the studies described here, but please indicate the origin of the work by citing this blog URL as an electronic web citation when it is appropriate to recognize and attribute the work of others.